By Dr. Shane Kurth, D.C., BCN · Medically reviewed by Dr. Shane Kurth, D.C., BCN · Last reviewed: August 2026
Editor’s note: This article explains how upper cervical spine dysfunction can contribute to TMJ symptoms. It does not cover all causes of TMJ disorder — dental and structural joint pathology require a dentist or oral surgeon.
Medical disclaimer: This content is educational only and is not medical or dental advice. Some TMJ disorders require dental or medical evaluation before chiropractic care is appropriate. For a medical emergency, call 911.
If you’re searching for a chiropractor for TMJ pain in Louisville, CO, here’s the honest version first: chiropractic may help — specifically when the cervical spine (upper neck) is contributing to jaw symptoms. The trigeminal nerve, which carries sensation from the jaw, and the upper cervical spinal nerves (C1–C3) converge at a shared brainstem structure called the trigeminocervical complex, and dysfunction at C1–C3 can refer pain into the jaw, face, and ear. Evidence for cervical manual therapy in TMJ disorders is promising but not yet definitive: systematic reviews show encouraging results for pain reduction and improved mouth opening, particularly with co-occurring neck pain. Chiropractic is an adjunct to — not a substitute for — dental evaluation.
Key Takeaways
- Jaw pain sometimes has a cervical spine component — the trigeminal and upper cervical nerves share a brainstem relay (the trigeminocervical complex) that can refer neck dysfunction into the jaw, face, and ear.
- Evidence for cervical manual therapy in TMJ disorders is promising but not yet definitive — systematic reviews (Calixtre 2015; La Touche 2020) show encouraging reductions in pain and jaw function, but high-quality definitive RCT evidence is not yet established.
- Chiropractic is most likely to help when TMJ symptoms co-occur with neck pain, tension headaches, and forward head posture — less so when structural joint pathology (disc displacement, arthritis, jaw locking) is the primary driver.
- A dental evaluation should come first if you have jaw locking, a sudden bite change, facial trauma history, or any red-flag sign listed in this article.
- At Apex Chiropractic in Louisville, TMJ-related care begins with a neurological assessment — SEMG, HRV, and digital X-ray — targeting the upper cervical segments, in partnership with your dental provider.
Why Jaw Pain Sometimes Starts in the Neck: The Trigeminocervical Connection
Most people think of jaw pain as a jaw problem. Occasionally it is — but a meaningful portion of TMJ presentations have a cervical spine component that goes unevaluated, because dental and medical systems typically assess these structures separately.
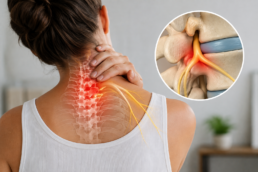
Here is the anatomy that connects them. The trigeminal nucleus caudalis — the brainstem structure that processes sensation from the face, jaw, and teeth — descends and overlaps with sensory input from the upper cervical nerves C1, C2, and C3. This convergence zone is the trigeminocervical complex. Because these inputs share the same relay neurons, the brain cannot always distinguish whether a pain signal originated from the jaw or the upper neck. A peer-reviewed anatomy review in Medicina confirms this convergence and its relevance to orofacial pain. The practical result: restriction or irritation at C1 or C2 can be felt as jaw aching, facial pressure, temple pain, or ear fullness — even when the TMJ joint itself shows no structural problem.

The jaw muscles add another layer. The masseter, temporalis, and pterygoids interface with this same trigeminocervical system, and upper cervical irritation can increase their resting tone — contributing to clenching, limited mouth opening, and mechanical load on the TMJ disc. Forward head posture compounds it: as the head shifts forward, cervical load increases and the jaw’s resting angle changes, adding compressive force to the TMJ. Whether posture drives TMD or TMD drives posture is bidirectional and unresolved — but clinically, the two travel together.
At our Louisville clinic, patients presenting with jaw pain and clicking often describe co-occurring neck tension, morning headaches, and upper trapezius tightness. These patterns suggest a cervicogenic contribution — a neck-driven component — that a dental evaluation alone would not capture. Our 3-Part NeuroTech Exam is designed to evaluate that cervical contribution with objective measures. An important scope note: this overlap explains why cervical chiropractic may help with TMD symptoms. It does not mean chiropractic treats the TMJ directly, and it does not replace dental evaluation for bite misalignment, disc pathology, or arthritis.
TMJ Disorder Explained: Symptoms, Causes, and the Cervical Role
Temporomandibular disorder (TMD) is an umbrella term for conditions affecting the temporomandibular joint — the hinge connecting the lower jaw to the skull, just in front of each ear — and the surrounding muscles and soft tissues. It is not a single diagnosis. TMD includes myofascial pain (muscle-driven), internal joint derangement (disc displacement), degenerative joint disease, and cervicogenic presentations where the neck is a primary driver.
Symptoms span a wider range than most patients expect, and several overlap with ear, sinus, and dental conditions — part of why TMD is frequently under-diagnosed:
- Jaw pain or soreness, especially on waking or after meals
- Clicking, popping, or grating sounds when opening or closing the mouth
- Limited mouth opening, or jaw deviation to one side during opening
- Tension-type headaches, particularly at the temples or base of the skull
- Ear fullness, stuffiness, or tinnitus without an ear-related diagnosis
- Facial aching along the cheekbone, jaw angle, or temple
- Neck pain and stiffness, particularly in the upper cervical region
- A sensation that your teeth are not fitting together quite right
Causes are similarly varied. Bruxism (nighttime grinding), bite misalignment, disc displacement, head or jaw trauma, prolonged dental procedures, degenerative joint changes, and cervical dysfunction with forward head posture are all recognized contributors. The National Academies of Sciences, Engineering, and Medicine’s 2020 report estimates that TMD affects roughly 5–12% of the U.S. population, with higher prevalence among women and adults aged 18–44. The breadth of this list is deliberate: not every TMD cause responds to the same intervention, which is why honest candidacy guidance matters.
Is Chiropractic Right for Your TMJ? An Honest Candidacy Guide
Chiropractic care is not the right fit for every TMJ presentation. A clinician who tells you otherwise is oversimplifying a multifactorial problem. The table below helps you orient toward the right first step.
| Cervicogenic TMD — Chiropractic May Help as Adjunct | Primarily Dental/Structural TMD — Dentist or Oral Surgeon First |
|---|---|
| Co-occurring neck pain or stiffness | Jaw locking (open or closed position) |
| Tension-type or morning headaches | Visible bite change or jaw deviation |
| Symptoms worsen with prolonged sitting or screen use | History of jaw trauma or facial fracture |
| Forward head posture noted on examination | Dental imaging showing disc displacement |
| Dentist has ruled out bite and structural joint pathology | Symptoms began immediately after a dental procedure |
| Stress-related jaw clenching with neck tension | Signs of degenerative joint disease on imaging |
If your presentation falls in the left column, the cervical spine contribution is the most plausible working hypothesis, and cervical manual therapy has the most supporting evidence for it — a chiropractic evaluation targeting the upper cervical segments is a reasonable next step, ideally alongside ongoing dental oversight. If it falls in the right column, the right first provider is your dentist or oral surgeon; chiropractic may play an adjunctive role later, after structural pathology is evaluated and stabilized, but it should not lead. Many patients occupy both columns: complex TMD often has dental and cervical components at once, and the literature increasingly supports co-management — dental splint therapy alongside cervical manual therapy, each addressing a different piece.
Want to know whether the cervical spine is contributing to your jaw symptoms? If you’re in Louisville, Lafayette, Superior, or greater Boulder County, our team offers a comprehensive neurological assessment to find out. Learn about our new-patient offer →
How Apex Evaluates TMJ-Related Neck Dysfunction in Louisville
At our Louisville clinic, a first visit for a TMJ-presenting patient does not begin with an adjustment. It begins with assessment.
The 3-Part NeuroTech Exam has three components. Digital X-ray of the cervical spine evaluates alignment and screens for structural contraindications. Surface electromyography (SEMG) is a non-invasive scan measuring electrical activity of the paraspinal muscles — a proxy for nervous system tone and muscle imbalance. Heart rate variability (HRV) measures autonomic function, reflecting stress load on the nervous system. For jaw-pain patients, we pay particular attention to C1, C2, and C3 — the upper cervical segments that interface with the trigeminocervical complex.

Torque Release Technique (TRT) is the adjustment method we use. Rather than manual rotational manipulation, it uses a hand-held spring-loaded instrument called an Integrator to deliver a precise, gentle impulse to a specific spinal segment — no forceful twisting, no audible crack. The goal is to reduce neurological interference at the identified level. For TMD patients with a cervicogenic component, the focus is typically the upper cervical spine and suboccipital musculature.
Why the SEMG baseline matters for TMJ patients. A patient with jaw clenching and morning headaches may not realize they are also carrying measurable paraspinal muscle imbalance at C1–C2 — visible on the scan as asymmetric electrical activity. This baseline gives an objective starting point, and follow-up scans track whether tone is normalizing. HRV adds autonomic context: bruxism and clenching are frequently stress-related, and chronically low HRV may reflect heightened sympathetic tone that contributes to jaw and neck guarding. This does not make chiropractic a treatment for stress — it means the care plan is built on a fuller picture. Read more about what to expect on your first visit before you come in.
Care is reassessed at defined intervals. TMJ-presenting patients receive a formal reassessment at 6–8 weeks using repeat SEMG and range-of-motion measures, compared to baseline. We do not offer guaranteed timelines or extended care commitments before seeing how your presentation responds.
What the Research Actually Says: Evidence for Manual Therapy and TMD
Patients deserve an honest account of the science — not a summary that makes the evidence sound stronger than it is.
A 2015 systematic review by Calixtre and colleagues in the Journal of Oral Rehabilitation found that manual therapy — particularly upper cervical manipulation and mobilization — showed the strongest evidence for symptom control and improved jaw movement among the manual therapy approaches studied in TMD patients, though results were limited by small samples and heterogeneous designs. A 2020 systematic review and meta-analysis by La Touche and colleagues in Pain Medicine found that cervical manual therapy and exercise produced statistically significant reductions in pain intensity and pressure pain sensitivity — suggesting that targeting the cervical spine, not just the jaw, can produce measurable effects. A 2024 review and meta-analysis by Bednarczyk and colleagues found cervical rehabilitation associated with significant short-term pain reduction in myogenic (muscle-driven) TMD — reinforcing the pattern that cervicogenic and myofascial presentations respond better than structural joint pathology.
| Study | Type | Finding | Evidence Level |
|---|---|---|---|
| Calixtre et al., J Oral Rehabil 2015 | Systematic review of RCTs | Upper cervical manipulation/mobilization showed strongest evidence for symptom control and improved jaw movement in TMD | Promising / Limited |
| La Touche et al., Pain Med 2020 | Systematic review + meta-analysis | Cervical manual therapy and exercise significantly reduced TMD pain intensity and pressure pain sensitivity | Promising / Limited |
| Bednarczyk et al., J Oral Rehabil 2024 | Systematic review + meta-analysis | Cervical rehabilitation associated with significant short-term pain reduction in myogenic TMD | Promising / Limited |
| Combined therapies (splint + manual therapy) | Multiple RCTs | Combination approaches show improvement; non-invasive approaches recommended before invasive procedures | Promising / Limited |
What this evidence means — and what it doesn’t. Current systematic reviews support the hypothesis that cervical manual therapy can reduce pain and improve jaw function in some TMD presentations, particularly myofascial and cervicogenic subtypes. Evidence is weaker for structural TMD involving disc displacement or arthritis. The optimal approach — chiropractic, dental treatment, or a combination — is not yet established by definitive high-quality RCT evidence. That is the honest state of the science. One caution: some content elsewhere presents small case series as near-universal proof of chiropractic effectiveness for TMD, but case series are the lowest level of clinical evidence — useful for generating hypotheses, not establishing effectiveness. The reviews cited here represent the highest available evidence tier, and they are appropriately cautious.
Dental Co-Care and the Chiropractic Role: How They Work Together in Louisville
A dentist or oral surgeon evaluates bite alignment, TMJ disc position, joint structure, and degenerative changes — assessments requiring dental imaging and expertise. A chiropractor evaluates cervical alignment, upper cervical restriction, paraspinal muscle tone, and neurological interference patterns. These are different lenses on a multifactorial problem, and the best outcomes in complex TMD typically involve both.
The night guard question deserves a straightforward answer. A dental splint reduces mechanical load on the TMJ by preventing tooth contact during sleep grinding — a valid, evidence-supported intervention for bruxism-related TMD. What it is not designed to address is cervical restriction, forward head posture, or neurological amplification through the trigeminocervical complex. If you have worn a night guard consistently and still have jaw aching, morning headaches, and neck tension, that is not necessarily evidence the splint failed — it may mean the cervical component was never evaluated. Both problems can coexist; the splint only addresses one.
If you have not yet had a dental evaluation for your jaw symptoms, that is step one. We ask about your dental history at intake. If findings suggest structural joint pathology outside our scope — disc displacement, significant bite asymmetry, joint locking — we will tell you directly and refer you back to your dentist or oral surgeon.
At Apex, we treat the cervical component of TMD in partnership with your dental provider, not in competition with them. The National Center for Complementary and Integrative Health notes that non-invasive approaches — including manual therapies — are generally recommended before more invasive interventions for TMD, consistent with how we position cervical chiropractic care at our Louisville clinic. Photobiomodulation (low-level light therapy) is a companion service available at our clinic that may suit some TMD presentations — ask our team whether it fits your case.
Red Flags: When to See Your Dentist or Oral Surgeon First
⚠️ See your dentist, oral surgeon, or physician before starting chiropractic care if you have:
- Jaw locking — your jaw is stuck open or closed and will not move voluntarily
- Sudden or severe facial swelling, especially with fever — possible infection requiring immediate medical attention
- History of jaw, face, or head trauma — fracture or joint damage needs imaging before any manual therapy
- Rapid changes in how your teeth fit together — a sudden bite change unrelated to dental work warrants dental imaging
- Suspected or confirmed disc displacement — internal joint derangement requiring MRI evaluation
- Symptoms escalating rapidly — pain worsening significantly over days, not responding to conservative measures
- Any suspicion of tumor or systemic disease affecting the jaw, neck, or salivary glands
Chiropractic care at Apex is appropriate for cervicogenic TMD presentations after these conditions have been ruled out or evaluated by the appropriate provider.
Chiropractic is also not the right primary treatment if your TMD is primarily structural — confirmed disc displacement on MRI, significant arthritis, or jaw locking require dental or surgical management first. It may serve as a helpful adjunct after appropriate dental treatment is established, but it does not substitute for it.
Frequently Asked Questions
Can a chiropractor actually help with TMJ pain?
A chiropractor may help with TMJ pain — specifically when the cervical spine is contributing to jaw symptoms. The upper cervical spinal nerves (C1–C3) share a brainstem relay with the trigeminal nerve; dysfunction in the upper neck can refer pain into the jaw, face, and ear. Systematic reviews (Calixtre 2015; La Touche 2020) show promising reductions in pain and jaw function, particularly for cervicogenic and myofascial presentations. Evidence is promising but not yet definitive, and chiropractic is best understood as an adjunct to — not a replacement for — dental evaluation.
How is the cervical spine connected to TMJ and jaw pain?
The trigeminal nerve (which innervates the jaw, teeth, and face) and the upper cervical nerves (C1, C2, C3) converge in the brainstem at the trigeminocervical complex. Because these inputs share the same relay neurons, the brain can interpret upper cervical dysfunction as jaw pain. This overlap explains why cervical restriction, forward head posture, and upper trapezius tension are common findings in TMD patients — and why addressing the neck can affect jaw symptoms even when the joint itself shows no structural pathology.
Should I see a dentist or chiropractor first for jaw pain?
Start with your dentist — especially if you have jaw locking, a sudden bite change, a history of jaw trauma, or symptoms that have never been dentally evaluated. Your dentist can rule out disc displacement, malocclusion, and structural joint pathology. If dental evaluation shows your bite and joint structure are intact but you still have jaw pain, morning headaches, and neck tension, a cervical evaluation at a neurologically-focused chiropractic clinic is a reasonable next step.
What does chiropractic treatment for TMJ look like at Apex?
At Apex Chiropractic in Louisville, we begin with a neurological assessment — the 3-Part NeuroTech Exam — covering digital X-ray for cervical alignment, SEMG (paraspinal muscle tone), and HRV (autonomic stress load). If upper cervical dysfunction is identified, we use Torque Release Technique: a low-force, instrument-assisted method with no forceful twisting and no audible crack. Care is formally reassessed at 6–8 weeks using objective SEMG measures compared to your baseline.
How many visits does it take to see improvement in TMJ symptoms?
There is no universal answer — outcomes depend on whether the cervical component is the primary driver, how long the problem has been present, and whether dental co-management is in place. The objective milestone we use is a formal 6–8-week reassessment comparing SEMG findings to your baseline. We do not offer guaranteed timelines or extended care commitments before seeing how your individual presentation responds.
Where is Apex Chiropractic located, and how do I book a first visit?
Apex Chiropractic is at 183 S Taylor Ave, Unit 162, Louisville, CO 80027 — serving Louisville, Lafayette, Superior, and the broader Boulder County area. Hours are Monday–Thursday 11:00 AM–1:00 PM and 3:00–6:00 PM; Friday closed. Call (720) 328-1790 or see our current new-patient specials to book your first visit — which begins with the 3-Part NeuroTech Exam, no adjustment until assessment is complete.
Visit Apex Chiropractic in Louisville
A first visit begins with a 3-Part NeuroTech Exam — neurological assessment before any adjustment, no pressure, and no long-term commitments before we see how your spine responds. Apex serves Louisville, Lafayette, Superior, Broomfield, Erie, and greater Boulder County.
See current new-patient specials or call to book.
Apex Chiropractic · 183 S Taylor Ave, Unit 162, Louisville, CO 80027 · (720) 328-1790
Hours: Mon–Thu 11:00 AM–1:00 PM & 3:00–6:00 PM · Fri closed
Sources
- Calixtre LB, Moreira RFC, Franchini GH, Alburquerque-Sendín F, Oliveira AB. Manual therapy for the management of pain and limited range of motion in subjects with signs and symptoms of temporomandibular disorder: a systematic review of randomised controlled trials. J Oral Rehabil. 2015;42(11):847–861. doi:10.1111/joor.12321
- La Touche R, Martínez García S, Serrano García B, et al. Effect of manual therapy and therapeutic exercise applied to the cervical region on pain and pressure pain sensitivity in patients with temporomandibular disorders: a systematic review and meta-analysis. Pain Med. 2020;21(10):2373–2384. PMID: 32181811. PubMed
- Pihut M, et al. Neural basis of etiopathogenesis and treatment of cervicogenic orofacial pain. Medicina. 2022;58(10):1324. PMC
- Bednarczyk M, et al. The effectiveness of cervical rehabilitation interventions for pain in adults with myogenic temporomandibular disorders: a systematic review and meta-analysis. J Oral Rehabil. 2024. doi:10.1111/joor.13671
- National Academies of Sciences, Engineering, and Medicine. Temporomandibular Disorders: Priorities for Research and Care. Washington, DC: National Academies Press; 2020. NCBI
- National Center for Complementary and Integrative Health. Temporomandibular Disorder. U.S. Department of Health and Human Services. NCCIH
About the Author
Dr. Shane Kurth, D.C., BCN is founder of Apex Chiropractic in Louisville, Colorado, and Board Certified in Chiropractic Neurology. He uses Torque Release Technique and objective SEMG/HRV assessment to evaluate and address the cervical spine’s contribution to TMJ disorders across greater Boulder County, working in partnership with patients’ dental and oral surgery providers.

Ready to See the Best Chiropractor in Louisville, CO?
Apex Chiropractic believes in thriving through life, not suffering in it. We believe that the activities that we want to partake in do not only desire but are necessary, just as necessary as our daily activities. In order to thrive in life and not suffer, we have to be completely in tune with our bodies. Schedule your appointment with us, today.