By Dr. Shane Kurth, D.C., BCN · Medically reviewed by Dr. Shane Kurth, D.C., BCN · Last reviewed: August 2026
Covers the cervicogenic component of post-concussion syndrome. Does not address neurological management of concussion itself, which requires physician evaluation.
Educational content only, not medical advice. See a physician before pursuing any care after a head injury. For a medical emergency, call 911.
Chiropractic care does not treat the brain injury of a concussion — that requires physician management. If you are looking for a post-concussion chiropractor in Louisville, any cervicogenic evaluation begins only after a physician has cleared you from neurological emergency. A randomized controlled trial by Schneider et al. (Br J Sports Med, 2014) suggests that cervicogenic rehabilitation — addressing the neck injury that commonly co-occurs with a head impact — may help reduce persistent symptoms like headache, dizziness, and neck pain in people already medically cleared but still symptomatic weeks after injury.
Key Takeaways
- Medical clearance is Step 1, always. Cervicogenic evaluation begins only after physician clearance. No exceptions.
- A concussion often involves two injuries. The force that injures the brain typically strains the cervical spine — separate injuries, separate recovery timelines.
- Evidence is emerging, not proven. Cervicogenic rehabilitation shows promise (Marshall 2015; Schneider 2014) for reducing time to clearance in slow-to-recover patients.
- Low-force matters. Torque Release Technique uses a handheld instrument — no cracking, no twisting.
- HRV and SEMG provide objective baselines, not concussion diagnostics.
If You’re Still Symptomatic Weeks After a Concussion, You’re Not Imagining It
Post-concussion syndrome (PCS) is symptoms persisting beyond the typical 7–10 day recovery window: headache, brain fog, memory difficulty, dizziness, fatigue, irritability, insomnia, nausea, and sensitivity to light and noise — a wide constellation that can make school, work, and daily life genuinely difficult.
If you or your teen athlete is at the 3–8 week mark and still not right, the data supports your experience. Research documents symptoms persisting beyond three months for 15–25% of adults and beyond four weeks in approximately 30% of children (Zemek et al., 2022). Children tend to experience longer and more severe post-concussive symptoms, and concussion is common among youth athletes across contact and collision sports.

This matters particularly for youth athletes across Boulder County — soccer, lacrosse, football, hockey, wrestling. These symptoms are real. Some of the contributors — specifically those arising from the neck — respond to evaluation and conservative care.
Medical Clearance for Post-Concussion Syndrome Is Non-Negotiable
A concussion is a brain injury. That sentence stands on its own because it has a specific clinical implication: physician evaluation and clearance must come before any chiropractic assessment. This is not a formality.
Neurological emergencies — intracranial hemorrhage, cerebral edema, skull fracture — can present with symptoms that overlap with a concussion. A chiropractic exam cannot detect them, and delay creates unacceptable risk. The CDC HEADS UP program states that only a healthcare provider should assess for possible concussion, and that return-to-sports is a medical decision.
At Apex, we do not accept post-concussion patients for cervicogenic evaluation until medical clearance is confirmed. If you come to us without clearance, our first action is to help you get there. Once cleared, the question becomes: is there a cervical component keeping your symptoms alive?
⚠️ Emergency Signs — Go to the ER Immediately
🚨 Do not book a chiropractor. Seek emergency care right now if you or your athlete experiences any of the following after a head injury:
- Worsening headache that does not improve or keeps getting worse
- Repeated vomiting
- Seizure or convulsion
- One-sided weakness, numbness, or paralysis
- Slurred speech or difficulty speaking
- Vision changes (double vision, loss of vision)
- Loss of consciousness, even briefly
- Increasing confusion, drowsiness, or difficulty waking up
These are signs of a potentially serious brain injury. Call 911 or go to the nearest emergency department immediately. Reference: CDC HEADS UP Concussion Program.
The Cervicogenic Connection: Why the Neck Often Keeps Symptoms Going
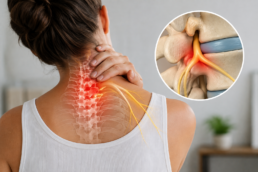
A single head impact typically produces two simultaneous injuries, not one. The rapid acceleration-deceleration force that causes the brain to move inside the skull applies the same force to the cervical spine — a whiplash-type strain, often concentrated in the upper cervical region (C1–C3), at the same moment as the brain injury. Two injuries, one hit, two separate recovery timelines.
Marshall, Vernon, Leddy, and Baldwin (Phys Sportsmed, 2015) proposed that cervical spine dysfunction from this concomitant whiplash-type injury is a potential and treatable cause of PCS. They described cervicogenic PCS as a clinically distinct subtype: the brain injury has resolved, but the cervical injury has not, and persistent headache, dizziness, and neck pain are being driven by the neck — not the brain. Schneider et al. tested this directly: their RCT enrolled athletes still symptomatic beyond 10 days post-injury and found cervicovestibular rehabilitation was associated with faster medical clearance compared to rest alone.
Cervicogenic headache typically originates at the base of the skull, worsens with neck movement, and is accompanied by neck stiffness or tenderness — often one-sided. This pattern differs from vestibular/ocular PCS subtypes and primary migraine.
Some providers claim upper cervical adjustment “restores blood flow and cerebrospinal fluid flow” after a concussion. These mechanistic claims go well beyond what peer-reviewed literature supports. The honest framing is narrower: cervical dysfunction may contribute to persistent PCS symptoms, and addressing it as part of a multidisciplinary plan has emerging evidence support.
How We Assess for Cervicogenic Involvement at Apex Chiropractic in Louisville
Before any cervicogenic care begins, one clinical question must be answered objectively: is the neck involved, and is this patient an appropriate candidate?
Heart Rate Variability (HRV) provides a window into autonomic nervous system function. Pertab et al. (2018) identified autonomic dysfunction as a recognized marker of PCS; Lynall et al. (2016) identified HRV as an emerging biomarker during exertion after sport-related concussion. HRV is not a diagnostic tool for concussion — it is one objective data point that allows tracking change over time.
Surface Electromyography (SEMG) maps paraspinal muscle tension that may reflect upper cervical joint dysfunction. In cervicogenic PCS, SEMG may reveal asymmetric activity in the upper cervical region consistent with joint irritation or protective guarding. In our Louisville clinic, patients often arrive describing a “tight neck” alongside other PCS symptoms — SEMG provides an objective map of where that tension lives.

Dr. Kurth’s clinical assessment also includes range-of-motion testing, cervical joint palpation, and relevant neurological screening as part of the 3-Part NeuroTech Exam. This is a cervicogenic dysfunction screening, not a concussion diagnosis — conducted only after medical clearance is confirmed.
Already medically cleared and still symptomatic? Call (720) 328-1790 or see what your first visit includes.
Torque Release Technique — Why Low-Force Matters After a Head Injury
A common question from parents of concussed athletes: “Is it safe to adjust someone’s neck after a brain injury?” The short answer is we don’t use high-velocity thrusts. Torque Release Technique (TRT) is an instrument-assisted, low-force method that delivers precise, gentle inputs to specific spinal segments using a handheld instrument called an Integrator. No high-velocity thrust, no forceful manipulation, no twisting, no cracking sounds. The applied force is calibrated and reproducible.
This matters for post-concussion patients because the nervous system is already dysregulated after a head injury. Forceful manual manipulation introduces mechanical stress that is clinically counterproductive at this stage. TRT’s instrument-assisted delivery minimizes that afferent load while still providing the segmental stimulus needed to address cervical dysfunction.
Essential calibration: TRT has not been specifically studied in post-concussion populations in randomized trials. The evidence for low-force cervical intervention in cervicogenic PCS is the Schneider RCT and Marshall review — neither tested TRT by name. The claim is that TRT’s instrument-assisted, low-force delivery is an appropriate application of the cervicogenic intervention principle those studies support — not that TRT itself has a dedicated PCS evidence base.
How Chiropractic Fits Into a Return-to-Play and Return-to-Learn Plan
The CDC HEADS UP Return to Play Progression is built on a single principle: an athlete returns to sports practices only with the approval and under the supervision of their healthcare provider, each step taking a minimum of 24 hours. The decision at each step belongs to the physician.
Cervicogenic evaluation at Apex fits at a specific point in this framework: athletes medically cleared but still symptomatic at Step 1 or early Step 2, with ongoing occipital headache, neck stiffness, or cervicogenic dizziness. Return-to-learn follows a parallel track: many teens are placed on modified school schedules because cognitive load, screen sensitivity, and noise sensitivity make a full day unmanageable. If a cervical component is adding to the headache burden that makes returning to class harder, it is worth asking.
Physicians, sports medicine providers, and certified athletic trainers in Boulder County working with post-concussion patients with cervicogenic features are welcome to inquire about co-management. Our scope is narrow (the cervical component), our approach is low-force, and our assessments are documented. One honest boundary: cervicogenic care does not accelerate brain healing — it addresses the separate cervical injury. Physician clearance is still required for each return-to-play step regardless of how cervical symptoms respond.
Who Is — and Isn’t — a Candidate for Cervicogenic Evaluation After a Concussion
Good candidates share these features: medical evaluation has occurred; no acute neurological emergency identified; a physician has provided explicit clearance for non-neurological adjunctive care; symptoms have persisted beyond two to four weeks; symptoms include cervicogenic features (headache at base of skull or one-sided, worsening with neck movement, neck stiffness, cervicogenic dizziness); no active neurological deficits present.
Not candidates at this time: any active neurological symptoms not yet medically evaluated; acute phase (within 7–10 days) without complete workup; active red-flag symptoms per the box above; diagnosed cervical instability or fracture; children under 12 (case-by-case only). If PCS symptoms are primarily vestibular or ocular without cervicogenic features, a vestibular specialist is the appropriate next stop. If mood disruption dominates, mental health co-care is the priority.
| Situation | Recommended Next Step |
|---|---|
| Head injury, acute phase (< 2 weeks) | See physician or urgent care; do not start chiropractic yet |
| Medically cleared, symptoms fully resolved | Monitor with physician; no chiropractic intervention needed |
| Medically cleared, still symptomatic at week 3+ with neck/headache features | Cervicogenic evaluation at Apex may be appropriate; call first to discuss |
| Active neurological symptoms (weakness, speech changes, vision loss) | Emergency care — do not delay |
| Symptoms primarily dizziness/visual without neck symptoms | Vestibular specialist or neuro-ophthalmology referral is the priority |
| Psychological/mood symptoms dominating | Mental health or neuropsychology co-care; chiropractic may complement, not lead |
Working With Your Care Team in Louisville and Boulder County
Apex’s role is a single defined component of a multidisciplinary plan: the cervicogenic piece. The physician leads. The certified athletic trainer tracks return-to-play staging. Mental health providers support mood and cognitive load. Physical therapists address vestibular and motor rehabilitation. Dr. Kurth evaluates and addresses upper cervical dysfunction when indicated by objective assessment.
For adults, the same evaluation model applies to post-concussion presentations from a motor vehicle accident, workplace incident, or fall. If your concussion resulted from a car crash, chiropractic care for auto injuries describes that pathway. If you’re unsure whether your situation fits what we do, contact our Louisville office.
Frequently Asked Questions
Q: Can a chiropractor help with post-concussion syndrome?
A chiropractor does not treat the brain injury of a concussion — that requires physician management. Emerging research supports cervicogenic rehabilitation as an adjunct for medically cleared patients still symptomatic weeks after injury (Schneider et al., 2014). At Apex, cervicogenic evaluation begins only after physician clearance.
Q: Is it safe to see a chiropractor if I still have concussion symptoms?
It depends on your recovery stage. Emergency signs — worsening headache, repeated vomiting, seizure, one-sided weakness, vision changes — require the ER, not a chiropractor. If you’re medically cleared and still have neck pain or movement-worsened headache, a low-force cervicogenic evaluation using TRT is generally considered appropriate within a co-managed recovery plan. We always confirm physician clearance first.
Q: What does a cervicogenic headache after a concussion feel like?
It typically starts at the base of the skull and radiates toward the forehead, temple, or behind one eye. It often worsens with neck movement or prolonged sitting, with neck stiffness or tenderness at the upper cervical joints. Unlike migraine, it rarely presents with aura, tends to be one-sided and position-dependent, and often improves when you find a comfortable neck position.
Q: What are the red-flag symptoms after a concussion that require emergency care?
Go to the ER immediately — do not book a chiropractor — for: worsening headache, repeated vomiting, seizure, one-sided weakness or numbness, slurred speech, vision changes, increasing confusion, or brief loss of consciousness. These may indicate intracranial hemorrhage or another serious brain injury.
Q: How long does post-concussion syndrome last?
In 80–90% of cases, symptoms resolve within two weeks, though recovery is somewhat slower for adolescents. Symptoms persist beyond three months in 15–25% of adults and beyond four weeks in about 30% of children (Zemek et al., 2022). The cervicogenic component is one of several potentially treatable contributors — Apex evaluates the cervical piece, not the full recovery timeline.
Q: How do I see Dr. Kurth at Apex Chiropractic in Louisville for a post-concussion evaluation?
Apex Chiropractic is at 183 S Taylor Ave, Unit 162, Louisville, CO 80027. Call (720) 328-1790. Hours: Mon–Thu 11:00 AM–1:00 PM and 3:00–6:00 PM; closed Friday. Confirm physician clearance before scheduling. New patients can review current specials online.
Visit Apex Chiropractic in Louisville
A first visit begins with objective assessment — HRV, SEMG, and clinical neurological screening — to determine whether cervicogenic care is appropriate. Apex serves Louisville, Superior, Lafayette, Erie, Broomfield, and greater Boulder County.
See current new patient specials or call to book.
Apex Chiropractic · 183 S Taylor Ave, Unit 162, Louisville, CO 80027 · (720) 328-1790
Hours: Mon–Thu 11:00 AM–1:00 PM & 3:00–6:00 PM · Fri closed
Sources
- Marshall CM, Vernon H, Leddy JJ, Baldwin BA. “The role of the cervical spine in post-concussion syndrome.” Phys Sportsmed. 2015;43(3):274–84. PubMed
- Schneider KJ, Meeuwisse WH, Nettel-Aguirre A, et al. “Cervicovestibular rehabilitation in sport-related concussion: a randomised controlled trial.” Br J Sports Med. 2014;48(17):1294–8. PubMed
- Pertab JL, et al. “Concussion and the autonomic nervous system: an introduction to the field and the results of a systematic review.” NeuroRehabilitation. 2018;42:397–427. PubMed
- Lynall RC, et al. “Heart rate variability of athletes across concussion recovery milestones: a preliminary study.” J Athl Train. 2016;51(6). PubMed
- Zemek R, et al. “Epidemiology of paediatric concussion.” BMC Pediatrics. 2022. PMC
- CDC HEADS UP: Responding to a Sports-related Concussion. cdc.gov/heads-up
- CDC HEADS UP: Return to Play Progression. cdc.gov/heads-up
About the Author
Dr. Shane Kurth, D.C., BCN is founder of Apex Chiropractic in Louisville, Colorado, and Board Certified in Chiropractic Neurology. He uses Torque Release Technique and objective SEMG/HRV assessment for medically cleared post-concussion patients with cervicogenic features across greater Boulder County, coordinating with physicians, sports medicine providers, athletic trainers, and mental health clinicians as clinically appropriate.

Ready to See the Best Chiropractor in Louisville, CO?
Apex Chiropractic believes in thriving through life, not suffering in it. We believe that the activities that we want to partake in do not only desire but are necessary, just as necessary as our daily activities. In order to thrive in life and not suffer, we have to be completely in tune with our bodies. Schedule your appointment with us, today.