By Dr. Shane Kurth, D.C., BCN · Medically reviewed by Dr. Shane Kurth, D.C., BCN · Last reviewed: August 2026
Written by the Apex Chiropractic clinical team to help Louisville-area patients distinguish cervicogenic headache from primary migraine.
Educational content only, not medical advice. For severe, sudden, or unusual headaches, seek medical attention promptly. Chiropractic is not appropriate for every headache type or patient. For a medical emergency, call 911.
For Louisville patients asking whether a chiropractor can help with chronic migraines, the honest answer depends on which type of headache is present. Chiropractic care is a legitimate option for cervicogenic headache — head pain originating from the neck — where moderate-level evidence supports spinal manipulation. For primary migraine, a neurological condition originating in the brain, evidence is mixed and rated low-to-moderate certainty; chiropractic is best considered a complementary option alongside neurologist-guided care, not standalone or first-line. The key question is which type of headache you are dealing with.
Key Takeaways
- Cervicogenic headache (neck-origin) has moderate-level research support for chiropractic spinal manipulation (Bryans et al., 2011, JMPT).
- For primary migraine, evidence is mixed and low-to-moderate certainty; the 2025 literature includes a systematic review finding very low certainty and a published rebuttal questioning that review’s methodology.
- Cervicogenic headache and migraine can look nearly identical — and can occur simultaneously in the same patient. Accurate assessment is essential.
- At Apex, evaluation begins with the NeuroTECH Exam (HRV and SEMG baselines), not manipulation — care recommendations are driven by assessment findings.
- Sudden severe headache, headache with fever and stiff neck, vision changes, or facial numbness: go to the ER, not a chiropractor.
⚠️ Red Flag Headache Symptoms — When to Go to the ER
🚨 Seek immediate emergency care — call 911 or go to the ER — if you experience any of the following:
- A sudden, severe headache that is the worst of your life (“thunderclap headache”) — even if it resolves quickly
- Headache with fever, stiff neck, or sensitivity to light (possible meningitis)
- Headache with confusion, difficulty speaking, facial drooping, arm or leg weakness, or vision changes (possible stroke)
- New headache in someone over age 50 with no prior headache history
- Headache following a head injury, even a mild one
- Headache with a progressively worsening pattern over days or weeks
- Headache with any new neurological symptom you have never experienced before
These are not chiropractic cases. They require immediate physician evaluation. If in doubt, go to the ER.
The ICHD-3 classification system includes explicit criteria for secondary headaches requiring urgent evaluation, and every presentation above falls into that category.
Migraine vs. Cervicogenic Headache: Why the Distinction Changes Everything
Primary migraine is a neurological headache disorder — its origin is in the brain. Episodes typically involve moderate-to-severe unilateral, pulsating pain lasting 4–72 hours, often with nausea, photophobia, or phonophobia. The trigeminal nerve and cortical spreading depression are both involved. ICHD-3 characterizes it as a primary disorder.
Cervicogenic headache is a secondary headache — caused by dysfunction in the cervical spine or neck soft tissues, with pain referred to the head. According to Chaibi and Russell’s population-level analysis, cervicogenic headache affects approximately 1–4.6% of the general population. It typically presents as unilateral pain originating in the occipital or suboccipital region, worsening with neck movement.

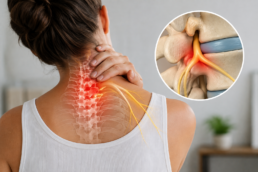
Neck problems cause head pain through the trigeminocervical nucleus — the upper cervical region where sensory fibers from the trigeminal nerve converge with sensory fibers from upper cervical nerve roots (C1–C3). Bogduk first characterized this convergence (1992); Biondi and follow-up work elaborated how dysfunction at those levels generates referred head pain that can mimic migraine. Crossed wiring: the brain receives a signal from the neck and processes part of it as coming from the head.
This overlap creates a diagnostic challenge. Cervicogenic headache can trigger nausea and photophobia — features most patients associate exclusively with migraine. A significant number of patients carry a migraine diagnosis when a cervical component is the primary driver, and both conditions can co-exist. Clinical signals that may suggest a cervical component: headache triggered by specific neck movements; pain beginning at the base of the skull and spreading forward; restricted cervical range of motion; concurrent neck pain; headaches worsening with sustained forward head posture. These are signals, not a diagnosis.
Evidence Review: What Research Supports for Chiropractic and Headaches
The honest answer is: it depends on which headache type.
For cervicogenic headache, evidence is moderate. Bryans and colleagues’ evidence-based chiropractic guidelines for adult headache (JMPT, 2011) found that spinal manipulation is recommended for cervicogenic headache and that joint mobilization or deep neck flexor exercises may also improve symptoms — overall evidence did not exceed a moderate level. A landmark RCT by Jull and colleagues (Spine, 2002) found manipulative therapy and specific low-load exercise reduced headache frequency and intensity at short- and long-term follow-up. The NCCIH cites a review of seven studies (601 participants) finding spinal manipulation may reduce cervicogenic headache frequency and intensity.
For primary migraine, the picture is more complicated. NCCIH cites a 2019 review of six studies (677 participants) suggesting spinal manipulation may reduce migraine days and intensity — overall certainty rated low. A 2025 systematic review by Ceballos-Laita and colleagues (EJIM) concluded evidence certainty was very low across headache types. A published response by Scott and Trager (EJIM, 2025) highlighted methodological limitations and questioned whether that review’s null conclusions were warranted. Both positions exist in the current literature. Clinically: chiropractic may help some migraine sufferers, the evidence does not yet allow confident predictions about who and by how much, and it should be used alongside — not instead of — neurologist-guided care for anyone with a diagnosed primary migraine disorder.
Transparency note: most of this research studies high-velocity, low-amplitude (HVLA) spinal manipulation. Apex uses Torque Release Technique (TRT) — a low-force, instrument-assisted method distinct from HVLA. TRT’s specific evidence base for headache treatment is limited. We apply it within a neurologically-based care framework, drawing context from established literature on cervical spinal manipulation — but do not claim that evidence as specific proof of TRT’s efficacy for any headache type.
| Headache Type | Evidence Level for Chiropractic | Recommended Framing |
|---|---|---|
| Cervicogenic headache | Moderate | Spinal manipulation recommended; may reduce frequency and intensity |
| Primary migraine | Mixed / low-to-moderate certainty | Complementary alongside neurologist guidance; not first-line; evidence actively contested in 2025 literature |
| Tension-type headache | Equivocal | Spinal manipulation not recommended for episodic TTH; low-load craniocervical mobilization may benefit chronic TTH |
| Cervicogenic + migraine co-presenting | Emerging | Cervical component may be addressable; migraine component requires medical co-management |
How Apex Evaluates Chronic Headache Patients in Louisville
At Apex, no adjustment is performed before a thorough assessment. That sequence — assess first, adjust based on findings — matters particularly for headache patients.
The foundation is the 3-Part NeuroTECH Exam. Heart-rate variability (HRV) — a measure of nervous system adaptive tone — is recorded as a baseline. Chronic pain tends to dysregulate HRV; tracking it provides an objective marker beyond symptom self-report. Surface electromyography (SEMG) measures paraspinal muscle electrical activity at rest, identifying tension, asymmetry, or guarding at specific spinal levels. In headache patients, elevated SEMG readings in the upper cervical region are common. Digital cervical imaging, when clinically indicated, adds structural context.
We commonly see headache patients in our Louisville clinic who have managed with OTC or prescription medication for months or years before seeking chiropractic assessment. One consistent pattern: elevated upper cervical SEMG readings in patients describing headaches that begin at the base of the skull and wrap forward toward the eye or temple. If the exam does not identify a meaningful cervical contribution, we say so directly.
Considering an assessment? Call (720) 328-1790 or see what your first visit includes.
Why Low-Force Torque Release Technique Matters for Headache Patients
Torque Release Technique is a low-force, instrument-assisted chiropractic method. Adjustments are delivered using the Integrator — a precise, spring-loaded handheld instrument — without high-velocity thrust, cervical rotation, or audible “cracking.” NCCIH notes that mild side effects such as temporary increased pain are common after spinal manipulation. TRT bypasses that concern structurally — no high-velocity cervical thrust — making it a viable option for patients hesitant about neck manipulation and for those in more acute headache phases.
The honest caveat: TRT’s specific evidence base for headache treatment is limited. The moderate-level evidence supporting cervical spinal manipulation for cervicogenic headache — from the Bryans guidelines and Jull RCT — provides surrounding context but cannot be applied as direct proof of TRT’s efficacy.
Who Is — and Isn’t — a Good Candidate for Chiropractic Headache Care
Patients most likely to benefit share features like: headache triggered or worsened by specific neck movements; pain beginning in the occipital or suboccipital region; restricted cervical range of motion; concurrent neck pain and headache; headaches worsening with sustained forward head posture; or onset following a cervical injury such as whiplash (with medical clearance established). Patients seeking a non-pharmacological complementary option alongside existing migraine management — with a cervical component confirmed on exam — are also reasonable candidates.
Patients less likely to benefit: Pure vestibular migraine with no cervical component is primarily neurological. Migraine with prominent or changing aura warrants neurology evaluation first. Hemiplegic migraine is managed medically. Active inflammatory conditions affecting the cervical spine require imaging and physician clearance first. Anyone with the red-flag symptoms above requires physician evaluation.
When we refer: If the exam does not identify a cervical contribution, we say so directly. We maintain collaborative relationships with Boulder County-area neurologists. Co-care is the norm for mixed presentations — chiropractic addressing a cervical component alongside a neurologist managing a diagnosed primary migraine disorder is a coherent combination.
Your First Headache Consultation at Apex Chiropractic in Louisville, CO
The first visit begins with a detailed intake focused on headache history: onset, frequency, duration, triggers, prior treatments, current medications, and co-diagnoses. Then the 3-Part NeuroTECH Exam: HRV baseline, SEMG scan, and clinical orthopedic and neurological assessment of the cervical spine. Cervical digital imaging follows if history and exam findings indicate it. The visit concludes with a review of findings — Dr. Kurth explains what was found and whether chiropractic care is the appropriate recommendation. If it is not, that conversation happens during the first visit, not after weeks of care.
| Phase | Typical Timeframe | What to Expect |
|---|---|---|
| Assessment and baseline | Visit 1 (~90 min) | Full NeuroTECH Exam; adjustment only if clinically appropriate |
| Initial care | Weeks 1–4 | Early neurological and symptom response; frequency and intensity tracking begins |
| Progress evaluation | Weeks 4–6 | HRV and SEMG re-scan; findings compared to baseline; care plan adjusted |
| Intermediate care | Weeks 6–12 | Many patients notice change in cervicogenic headache frequency or intensity; co-care maintained for mixed presentations |
| Maintenance | Beyond week 12 | Individualized based on ongoing findings; some patients reach stable maintenance, others taper off |
Illustrative ranges; they vary by individual and depend on assessment findings. Not guaranteed outcomes.
Frequently Asked Questions
Q: Can a chiropractor help with chronic migraines?
For chronic headaches with a confirmed cervical component — cervicogenic headache — moderate-level evidence supports spinal manipulation (Bryans et al., 2011). For primary migraine, which originates in the brain rather than the neck, evidence is mixed and rated low-to-moderate certainty; chiropractic is best used alongside neurologist-guided care, not standalone or first-line.
Q: What is the difference between a cervicogenic headache and a migraine?
Migraine is a primary neurological disorder originating in the brain, typically with pulsating unilateral pain, nausea, and sensitivity to light or sound. Cervicogenic headache is a secondary headache caused by cervical spine dysfunction; pain is referred via the trigeminocervical pathway, where upper cervical nerve roots (C1–C3) converge with descending trigeminal fibers. Both conditions can co-exist.
Q: What are the red flag symptoms that mean a headache needs emergency care?
Seek emergency care immediately for: a sudden “worst headache of your life”; headache with fever and stiff neck; headache with confusion, vision changes, facial drooping, or limb weakness; new headache pattern after age 50; headache after a head injury; or any progressively worsening headache. These require physician evaluation, not a chiropractic appointment.
Q: Is Torque Release Technique (TRT) safe for headache patients?
TRT is a low-force, instrument-assisted technique that does not involve high-velocity cervical thrust. Because it avoids forceful neck adjustment, it is often well-tolerated by headache patients. Whether TRT is appropriate for any individual is determined after a full clinical assessment.
Q: How many visits does it typically take to see improvement?
Individual response varies and cannot be predicted in advance. Research on cervicogenic headache dose-response suggests a meaningful response may emerge across 8–18 sessions depending on the individual and degree of cervical involvement (Haas et al., 2010). See a neurologist for red-flag symptoms, significant aura, hemiplegic migraine, or a changing headache pattern.
Q: How do I visit Apex Chiropractic in Louisville for a headache consultation?
Apex Chiropractic is at 183 S Taylor Ave, Unit 162, Louisville, CO 80027. Call (720) 328-1790. Hours: Mon–Thu 11:00 AM–1:00 PM and 3:00–6:00 PM; closed Fridays. New patients can review current specials online.
Visit Apex Chiropractic in Louisville
A first visit begins with a full NeuroTECH Exam, digital imaging if clinically indicated, and an honest conversation about fit. Apex serves Louisville, Superior, Lafayette, Erie, Broomfield, Westminster, and greater Boulder County.
See current new patient specials or call to book.
Apex Chiropractic · 183 S Taylor Ave, Unit 162, Louisville, CO 80027 · (720) 328-1790
Hours: Mon–Thu 11:00 AM–1:00 PM & 3:00–6:00 PM · Fri closed
Sources
- Bryans R, Descarreaux M, et al. “Evidence-based guidelines for the chiropractic treatment of adults with headache.” J Manipulative Physiol Ther. 2011;34(5):274–89. PubMed
- Jull G, Trott P, et al. “A randomized controlled trial of exercise and manipulative therapy for cervicogenic headache.” Spine. 2002;27(17):1835–43. PubMed
- NCCIH. “Spinal Manipulation: What You Need to Know.” NCCIH
- Biondi DM. “Cervicogenic headache: mechanisms, evaluation, and treatment strategies.” J Am Osteopath Assoc. 2000;100(9 Suppl):S7–14. PubMed
- Biondi DM. “Cervicogenic headache: a review of diagnostic and treatment strategies.” J Am Osteopath Assoc. 2005;105(4 Suppl 2):16S–22S. PubMed
- Bogduk N. “The anatomical basis for cervicogenic headache.” J Manipulative Physiol Ther. 1992;15(1):67–70. PubMed
- Haas M, et al. “Dose response and efficacy of spinal manipulation for chronic cervicogenic headache.” Spine J. 2010;10(2):117–28. PubMed
- Chaibi A, Russell MB. “Manuscript on the classification, diagnosis, epidemiology, and mechanism of headache.” BMC Research Notes. 2017. PMC
- Ceballos-Laita L, et al. “Is chiropractic spinal manipulation effective for cervicogenic, tension-type, or migraine headaches? A systematic review.” Eur J Integr Med. 2025. ScienceDirect
- Scott ZE, Trager RJ. “Opinion: A 2025 review of chiropractic spinal manipulation for headaches was bound for null results.” Eur J Integr Med. 2025.
- International Classification of Headache Disorders, 3rd edition (ICHD-3). ichd-3.org
About the Author
Dr. Shane Kurth, D.C., BCN is founder of Apex Chiropractic in Louisville, Colorado, board-certified in chronic intractable pain and neuropathy. He uses Torque Release Technique and objective SEMG/HRV assessment for chronic headache and cervicogenic pain patients throughout Louisville, Superior, Lafayette, Broomfield, Erie, and greater Boulder County, coordinating with neurologists and primary care physicians as clinically appropriate.


Ready to See the Best Chiropractor in Louisville, CO?
Apex Chiropractic believes in thriving through life, not suffering in it. We believe that the activities that we want to partake in do not only desire but are necessary, just as necessary as our daily activities. In order to thrive in life and not suffer, we have to be completely in tune with our bodies. Schedule your appointment with us, today.