By Dr. Shane Kurth, D.C., BCN · Medically reviewed by Dr. Shane Kurth, D.C., BCN · Last reviewed: July 2026
Evidence-based non-surgical options for sciatica — what the research supports and when conservative care isn’t the right first step. Sciatica with bladder/bowel changes, saddle numbness, or rapidly worsening leg weakness is a medical emergency — see the red-flag section below.
Educational content only — not medical advice. Consult a qualified healthcare provider before starting, changing, or stopping any treatment. If you are experiencing severe or worsening symptoms, seek care today.
Sciatica is pain that radiates from the lower back through the buttock and down one leg along the path of the sciatic nerve. For the majority of people — especially when symptoms have been present for less than 12 weeks — it resolves without surgery. First-line non-surgical options with the strongest guideline support include spinal manipulation, physical therapy, targeted exercise, and anti-inflammatory medication. Evidence levels vary by treatment and by how long symptoms have persisted, and no single option works for everyone. This guide explains what the research supports, what it does not, and how to make an informed decision with your care team.
Key Takeaways
- Most sciatica resolves without surgery, particularly when symptoms have been present for less than 12 weeks and there are no red-flag signs.
- The ACP recommends spinal manipulation as a first-line nonpharmacologic option for LBP with leg symptoms (Ann Intern Med, 2017), alongside exercise, heat, and massage.
- Evidence levels vary: a 2025 network meta-analysis found large short-term effect sizes for spinal manipulation in chronic sciatica, but authors rated confidence very low.
- Cauda equina syndrome is the exception: new bladder/bowel loss, saddle numbness, or rapidly worsening bilateral leg weakness are surgical emergencies — go to the ER.
- Combinations outperform single modalities. Assessment plus spinal manipulation, PT, and medical co-care consistently produces better outcomes than any single approach.
What Is Sciatica, and Why Do Most Cases Resolve Without Surgery?
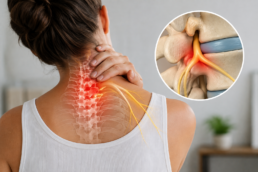
The sciatic nerve is the largest in the body, formed by roots L4 through S1. Those roots converge and travel through the buttock and down the back of each leg — which is why irritation at the source can produce symptoms reaching the foot. Sciatica is a radiculopathy — symptoms from nerve root irritation — not a diagnosis itself. Common causes: a herniated or bulging disc, a bone spur narrowing the exit space, or spinal stenosis.
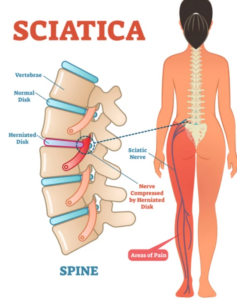
Not all leg pain is sciatica. Pain down the outer shin, into the groin, or unpredictably across both legs may suggest a different source — one reason clinical assessment matters. Most acute sciatica (under 12 weeks) improves substantially with conservative care; chronic cases often respond well to the right combination.
What the American College of Physicians recommends:
The ACP’s 2017 guideline (Ann Intern Med) recommends that patients with acute or subacute LBP, including associated leg symptoms, initially select nonpharmacologic treatment, with spinal manipulation among first-line options. For chronic LBP, spinal manipulation is likewise listed among initial nonpharmacologic choices.
⚠️ Red-Flag Warning Signs: When Sciatica Is a Medical Emergency
🚨 Stop reading and go to the emergency room if you experience any of the following:
- New loss of bladder or bowel control — inability to urinate, incontinence, or loss of the sensation that tells you when you need to go
- Saddle anesthesia — numbness in the inner thighs, groin, buttocks, or genital/perineal area (the area that would contact a saddle)
- Rapidly progressing leg weakness — weakness in one leg noticeably worse over hours or days; or new weakness in both legs simultaneously
- Bilateral leg pain — sciatica-type radiating pain in both legs at the same time
These are warning signs of cauda equina syndrome (CES) — a neurological emergency caused by severe compression of the nerve roots at the base of the spinal cord. Cleveland Clinic describes CES as requiring urgent MRI and, in most cases, emergency surgery. Delaying evaluation by even a few hours can affect long-term outcomes. Do not call a chiropractic clinic. Go to the emergency room or call 911.
Ordinary sciatica — one-sided leg pain, even severe — is not typically a medical emergency, though it warrants professional evaluation. We screen for these signs at every intake precisely because missing them would be a serious error. If none apply, the evidence for conservative care is encouraging.
The Evidence-Ranked Guide to Non-Surgical Sciatica Treatments
Each modality below carries an honest evidence tag — calibrated information is more useful than confident-sounding generalizations.
Spinal Manipulation / Chiropractic Care
Evidence level: Moderate (ACP first-line for LBP with leg symptoms)
The ACP guideline places spinal manipulation among first-line nonpharmacologic recommendations for acute, subacute, and chronic LBP with leg symptoms. The 2025 network meta-analysis (50 RCTs, 4,920 participants) found spinal manipulative therapy among interventions with the largest short-term leg pain reductions in chronic sciatica — authors rated confidence very low. Torque Release Technique care offers a low-force, assessment-driven approach for patients who cannot tolerate traditional high-velocity manipulation.
Physical Therapy and Exercise
Evidence level: Moderate–Strong
Targeted exercise — particularly nerve mobilization (“neural flossing”) with core stabilization — is among the best-supported conservative interventions. The 2025 meta-analysis found exercise plus neural mobilization comparable to spinal manipulation for short-term leg pain. Walking and gentle movement are appropriate; heavy loading and deep forward folds can aggravate an irritated nerve root. Supervised programs preferable to generic online routines.
NSAIDs (Anti-Inflammatory Medications)
Evidence level: Moderate
The ACP lists NSAIDs as the preferred pharmacologic option when drug therapy is desired. They address the inflammatory component of nerve root irritation and can make it easier to engage with other treatments. Your physician assesses appropriateness — there are GI and cardiovascular considerations with extended use.
Heat and Cold Therapy
Evidence level: Limited (symptom management)
Cold can reduce acute local inflammation in the first days; heat relaxes protective muscle spasm. Reasonable adjuncts in the first 1–2 weeks, not adequate as standalone care.
Epidural Steroid Injections (ESIs)
Evidence level: Moderate short-term; limited longer-term
ESIs deliver a corticosteroid near the affected nerve root to reduce periradicular inflammation. The 2025 meta-analysis found ESI effects diminished at medium and long-term follow-up. Administered by interventional pain specialists or physiatrists — not chiropractors — ESIs are an escalation option. For patients who have plateaued on conservative care, an injection may provide enough relief to re-engage with PT.
Acupuncture
Evidence level: Emerging/Limited for sciatica specifically
The ACP lists acupuncture among options for general LBP; evidence specifically for sciatica-related radicular pain is thinner. Reasonable pain-management adjunct.
Spinal Decompression Therapy
Evidence level: Emerging
Mechanical decompression uses traction-based technology to reduce intradiscal pressure. Evidence base still developing. For clearly disc-related sciatica, see what spinal decompression involves for candidacy and current research.
| Treatment | Evidence Level for Sciatica | Guideline Recommendation | Best For |
|---|---|---|---|
| Spinal manipulation | Moderate — ACP first-line for LBP with leg symptoms | ACP 2017; NCCIH resource | Acute, subacute, chronic |
| Physical therapy / exercise | Moderate–Strong | Multiple guidelines | All durations; supervised preferred |
| NSAIDs | Moderate | ACP 2017 (pharmacologic) | Short-term; physician-guided |
| Heat / Cold | Limited | Supportive care | First 1–2 weeks |
| Epidural steroid injections | Moderate short-term / limited long-term | Escalation option | Plateau after conservative care |
| Acupuncture | Emerging for sciatica | ACP 2017 (LBP) | Adjunct / co-care |
| Spinal decompression | Emerging | No major guideline yet | Specific disc candidacy |
How Spinal Manipulation Addresses Sciatic Nerve Irritation
Sciatica originates where nerve roots exit the lumbar spine — L4, L5, S1 most commonly. Poor segmental movement or asymmetric loading can contribute to mechanical compression and inflammatory stress on the nearby nerve root. Spinal manipulation aims to restore mobility, reduce protective muscle spasm, and decrease mechanical stress on the irritated root. The clinical effect earns a guideline recommendation; the pathways are not fully understood.
The 2017 ACP guideline places spinal manipulation among first-line nonpharmacologic recommendations. The NCCIH lists it as a nondrug approach for back pain with leg symptoms. The 2025 network meta-analysis in The Journal of Pain (50 RCTs, 4,920 participants) found spinal manipulative therapy among interventions with the largest short-term leg pain reductions, alongside exercise plus neural mobilization. Authors rated confidence very low.
The Assessment-Driven Intake
Apex intake includes:
- Digital X-ray analysis: structural baseline, contraindication screening, spinal-level confirmation
- Surface EMG (SEMG): maps muscle activation along the spine, identifying neurological stress at involved roots
- HRV (heart-rate variability): autonomic nervous system baseline for stress and load
This is the 3-Part NeuroTech Exam. Sciatica patients frequently show identifiable SEMG patterns — often asymmetric muscle guarding at L4–S1 on the side of leg pain. This baseline lets us track whether care is producing the neurological response we want, not just whether pain scores are improving.
Who Is — and Is Not — a Good Candidate
Honest candidacy is what a responsible clinician discusses with every new patient.
Chiropractic care (including TRT) is typically appropriate for:
- Acute or subacute sciatica (under 12 weeks) without progressive deficit
- Chronic sciatica without red flags, unresponsive to rest and medication
- Single-sided radiating leg pain without bowel/bladder or saddle-area changes
- Patients who cannot tolerate HVLA due to age, osteoporosis, pain sensitivity, or prior experience
- Patients who want to exhaust conservative options before imaging or injection
Chiropractic care is not the right first step for:
- Any cauda equina red-flag signs — immediate ER, not a chiropractic intake
- Rapidly progressive motor weakness (foot drop over hours to days) — urgent MRI first
- Known or suspected spinal fracture, tumor, or infection
- Severe disc sequestration with progressive deficit — orthopedic/neurosurgical consultation first
- Patients on anticoagulation — medical clearance needed
- Sciatica from non-musculoskeletal sources (pelvic/abdominal pathology) — specialist referral first
If unsure whether your symptoms are appropriate for chiropractic care, start with your PCP. We coordinate with PCPs, neurologists, and orthopedists — and will say directly if intake suggests imaging first.
Your Non-Surgical Treatment Timeline
Duration, severity, and underlying cause all affect how quickly sciatica resolves. The framework below reflects a commonly used stepwise approach — least invasive first, escalating only when a conservative trial has been given adequate time. Decision-support, not a guaranteed protocol.
| Phase | Timeframe | Recommended Approaches | When to Escalate |
|---|---|---|---|
| Acute | Weeks 1–4 | Gentle movement, ice/heat, NSAIDs (physician-guided), spinal manipulation, begin PT | Red-flag signs → ER; no improvement at 4 weeks |
| Subacute | Weeks 4–8 | Continue manipulation + PT; reassess neurological status; consider imaging if no improvement | Progressing weakness; bilateral symptoms; imaging + provider reassessment |
| Plateau/Escalation | Weeks 8–12 | Add or substitute: epidural steroid injection; intensive rehabilitation; reassess imaging | Surgical consultation if progressive deficit or 12 weeks failed conservative care |
| Surgical Consideration | Week 12+ | Surgical evaluation (not automatically surgery) if cauda equina, foot drop, or sustained failure | Orthopedic or neurosurgical referral |
“Twelve weeks” is a benchmark, not an absolute cutoff — some patients improve substantially between weeks 8 and 16. Surgery is most clearly indicated for progressive neurological deficit or cauda equina syndrome. Pain alone, even severe, is not a surgical indication when neurological function is stable. For imaging-confirmed disc involvement, spinal decompression is worth discussing with your care team.
Working With Your Medical Team: Chiropractic as Part of Co-Care
Chiropractic and medical care for sciatica address different components of the same problem. A PCP managing inflammation and monitoring neurological status, a PT building core stability, and a chiropractor addressing spinal-segment restriction each contribute something the others cannot. Loop in your PCP for persistent or worsening pain, NSAID considerations, or new neurological signs. Involve a neurologist or physiatrist for suspected ongoing nerve root compression not responding to conservative care, electrodiagnostic testing, or injection therapy. Involve an orthopedic or neurosurgical specialist when imaging shows severe stenosis or significant nerve root compromise, or with progressive neurological deficit — the purpose is evaluation, not automatic surgery.
At Apex, we communicate findings with referring providers, provide post-visit documentation, and facilitate referrals when intake suggests imaging first. Soft-tissue work and photobiomodulation therapy are available in-clinic as adjunctive co-care.
Frequently Asked Questions
Q: What is the most effective non-surgical treatment for sciatica?
No single treatment is universally most effective — the best option depends on duration, severity, and cause. The ACP places spinal manipulation among first-line nonpharmacologic options alongside exercise and PT. The 2025 network meta-analysis found spinal manipulation and exercise-plus-neural-mobilization showed the largest short-term reductions, though confidence was rated very low. Combinations outperform any single treatment.
Q: Can a chiropractor help with sciatic nerve pain?
Yes, for most patients with unilateral sciatica and no red-flag signs. Spinal manipulation is recommended in the ACP guideline for back pain with leg symptoms, and NCCIH lists it as a nondrug option. Patients with progressive weakness, bilateral symptoms, or bladder/bowel changes need emergency medical evaluation.
Q: How long does it take for sciatica to go away without surgery?
Most acute sciatica (under 12 weeks) improves meaningfully within 4–8 weeks of conservative care; chronic cases require longer. If symptoms are not meaningfully improving after 8–12 weeks of consistent care, the next step is imaging and reassessment — not necessarily surgery, but a fuller evaluation.
Q: What are the warning signs that sciatica needs emergency treatment?
Go to the ER immediately for loss of bladder or bowel control, inability to urinate, saddle anesthesia (numbness in inner thighs, groin, or genital area), rapidly worsening weakness in one or both legs, or bilateral radiating leg pain. These are signs of cauda equina syndrome — a neurological emergency requiring urgent MRI and likely surgery.
Q: What exercises make sciatica worse?
Deep forward folds under load, heavy deadlifts, toe-touches, bearing down or straining, prolonged sitting without lumbar support, and high-impact running during acute flare. Right exercises vary by root cause — ask your provider or PT first.
Q: How do I start chiropractic care for sciatica at Apex Chiropractic?
New patients begin with a comprehensive neurological assessment — digital X-ray, surface EMG, and HRV testing — before any adjustment. Apex is at 183 S Taylor Ave, Unit 162, Louisville, CO 80027. Call (720) 328-1790 or see our new patient offer.
Visit Apex Chiropractic in Louisville
New patients begin with a full neurological intake — digital X-ray, surface EMG, and HRV baseline — so Dr. Kurth understands what is driving your symptoms before any adjustment. See current new patient specials or call to book.
Apex Chiropractic · 183 S Taylor Ave, Unit 162, Louisville, CO 80027 · (720) 328-1790
Hours: Mon–Thu 11:00 AM–1:00 PM & 3:00–6:00 PM · Fri closed
Sources
- Qaseem A, et al. “Noninvasive Treatments for Acute, Subacute, and Chronic Low Back Pain: ACP Clinical Practice Guideline.” Ann Intern Med. 2017;166(7):514–530. acpjournals.org
- “Effectiveness of non-surgical interventions for patients with chronic sciatica: A systematic review with network meta-analysis.” The Journal of Pain. 2025. DOI: 10.1016/j.jpain.2025.105382
- NCCIH. “Spinal Manipulation: What You Need To Know.” nccih.nih.gov
- Cleveland Clinic. “Cauda Equina Syndrome.” clevelandclinic.org
About the Author
Dr. Shane Kurth, D.C., BCN is founder of Apex Chiropractic in Louisville, Colorado, board-certified in chronic intractable pain and neuropathy. An Auburn University microbiology graduate, he uses Torque Release Technique alongside coordinated conservative care. He treats patients throughout Louisville, Superior, Lafayette, Broomfield, Erie, and the greater Boulder area, coordinating with PCPs, neurologists, physiatrists, orthopedic surgeons, and PTs when multi-provider care is warranted.

Ready to See the Best Chiropractor in Louisville, CO?
Apex Chiropractic believes in thriving through life, not suffering in it. We believe that the activities that we want to partake in do not only desire but are necessary, just as necessary as our daily activities. In order to thrive in life and not suffer, we have to be completely in tune with our bodies. Schedule your appointment with us, today.