By Dr. Shane Kurth, D.C., BCN · Medically reviewed by Dr. Shane Kurth, D.C., BCN · Last reviewed: July 2026
This post explains nonsurgical spinal decompression: what the research shows and how to assess whether you may be a candidate.
This content is for educational purposes only and does not constitute medical advice. Please consult a qualified healthcare provider — chiropractor, physiatrist, orthopedic physician, or spine surgeon — before beginning or changing any treatment for a herniated disc.
Spinal decompression for a herniated disc — the nonsurgical, motorized traction-based approach — is one of the conservative options adults increasingly ask about before deciding whether to pursue surgery. The treatment is designed to reduce intradiscal pressure and create a gentle negative-pressure environment within the disc. That environment may allow displaced disc material to retract away from the affected nerve root. For lumbar disc herniation with radiculopathy — irritation or compression of a nerve root where it exits the spine — the evidence is emerging and promising. Small randomized controlled trials have shown statistically significant pain reduction and MRI-verified herniation volume change. However, most trials are small, the evidence base is not yet definitive, and this treatment is not appropriate for all herniation types or presentations. Some patients will need surgery regardless of their interest in conservative care.
Key Takeaways
- Evidence is emerging, not definitive. The strongest single study (Choi et al. 2022) was a 60-patient sham-controlled RCT showing significant pain reduction and MRI-verified herniation volume change. Larger multi-center trials are needed.
- Candidacy matters more than enthusiasm. Nonsurgical decompression is not appropriate for prior surgery at the affected level, spinal fracture, malignancy, active infection, advanced osteoporosis, or cauda equina symptoms.
- Herniation type affects fit. Bulges and protrusions are best-studied for conservative care. Extruded or sequestered discs typically warrant surgical consultation.
- Best as part of coordinated care. The Amjad et al. 2022 RCT found decompression plus PT superior to PT alone.
- Some patients need surgery. Rapidly progressive motor weakness, foot drop, cauda equina syndrome, or failure of 6–12 weeks of conservative care are indications for surgical consultation.
What Is Spinal Decompression for a Herniated Disc?
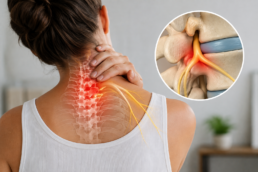
A herniated disc occurs when the soft inner nucleus pulposus pushes through a tear in the tougher outer annulus fibrosus, potentially compressing nerve roots and producing pain, numbness, or weakness radiating down the leg. Nonsurgical spinal decompression is a computer-controlled motorized traction system that applies calibrated distraction force to specific spinal segments to reduce intradiscal pressure.
The name causes confusion. Surgical decompression — laminectomy, microdiscectomy, discectomy — involves a surgeon removing bone or disc material under anesthesia. Nonsurgical decompression involves no incisions or anesthesia and no hospital stay; it is an outpatient procedure on a motorized table. It is not a massage, not passive weight-and-pulley traction, and not a chiropractic adjustment (see our Torque Release Technique page for how TRT differs). This post focuses on the lumbar spine, where most research has been conducted.

How Nonsurgical Spinal Decompression Works
The basis rests on intradiscal pressure dynamics. Controlled distraction creates a negative pressure environment within the disc — a “vacuum effect” — that may draw herniated material back toward the disc center and reduce nerve root compression. Computerized motorized decompression can drive pressure below −100 mmHg, a level conventional traction does not consistently reach (per background literature reviewed by Choi et al. 2022). Decompression is also thought to create a cyclical pumping effect promoting disc rehydration — a theoretical component not yet independently validated.
A session: you lie on a computer-controlled table, a harness or pelvic belt is secured around the lumbar spine, and the table applies pre-programmed distraction force at a specific angle over 20–45 minutes. Most patients describe gentle pulling rather than pain. Mild temporary soreness after early sessions is common.
At our Louisville clinic, before recommending decompression, we establish each patient’s neurological baseline using SEMG (surface electromyography) and HRV (heart rate variability). Patients whose nervous systems are highly guarded may benefit from a few low-force TRT adjustments first — a braced nervous system can resist the relaxation the table requires. See our 3-Part NeuroTech Exam page for baseline detail.
What the Research Actually Shows
Nonsurgical spinal decompression has a growing but not yet definitive evidence base. Most RCTs are small (under 100 participants) and use varying equipment and outcome measures. Here is what the three most-cited studies show.
Choi et al. 2022 (PMC9553669): Sham-controlled RCT of 60 patients with subacute lumbar disc herniation (4–12 weeks of symptoms). Decompression group received 10 sessions over 8 weeks; sham group received identical setup with no distraction force. Decompression group showed significantly lower leg pain at two months (p = 0.028) and MRI-measured herniation volume reduction. Strongest available evidence because sham design accounts for placebo. Limitations: small; subacute only; single center.
Amjad et al. 2022 (PMC8924735): RCT of 60 patients with lumbar radiculopathy compared decompression plus PT against PT alone. At four weeks, decompression-plus-PT was superior on pain, range of motion, endurance, disability, and quality of life. Supports decompression within coordinated care. Limitation: four-week follow-up.
Apfel et al. 2010 (PMC2912793): Retrospective cohort of 30 patients with chronic low back pain from disc herniation documented disc height increase from 7.5 to 8.8 mm (p < 0.001) and pain reduction from 6.2 to 1.6 on a 0–10 scale after six weeks. Limitations: retrospective, no control.
| Study | Design | N | Key Finding | Key Limitation |
|---|---|---|---|---|
| Choi 2022 | Sham-controlled RCT | 60 | Significant leg pain reduction; MRI-verified herniation volume reduction | Small; subacute only |
| Amjad 2022 | RCT | 60 | Decompression + PT superior to PT alone | 4-week follow-up |
| Apfel 2010 | Retrospective cohort | 30 | Disc height increased; pain reduced | No control group |
The honest summary: available evidence suggests decompression may provide meaningful relief for appropriately selected patients. Trial sizes are small and larger multi-center RCTs are needed. For context, the American College of Physicians’ 2017 clinical practice guideline recommends nonpharmacologic treatment for chronic low back pain including spinal manipulation. Nonsurgical decompression is not specifically named in that guideline but falls within the conservative-care spectrum — the ACP’s strong-recommendation language applies to exercise and spinal manipulation specifically, not decompression by name.
Are You a Candidate? A Clinical Checklist
Candidacy requires imaging review, clinical history, and neurological assessment. The following criteria — drawn from research exclusion criteria and standard contraindications — are the honest framework:
You May Be a Candidate If:
- You have a confirmed lumbar disc herniation (bulge or protrusion) on MRI or CT with back and/or leg symptoms
- Your herniation is subacute (4–12 weeks) or chronic
- You have not had prior surgery at the affected disc level
- You have mild to moderate neurological symptoms, not progressive motor weakness
- You are willing to combine conservative options
- Your overall health and bone density support the physical demands of the table
You Are NOT a Candidate If:
Drawn from Choi 2022 exclusion criteria and standard clinical contraindications:
- Prior surgery at the affected level (fusion, laminectomy, discectomy) — scar tissue and hardware make traction unpredictable
- Spinal fracture or compression fracture at the affected level
- Spinal malignancy involving the vertebrae or disc
- Active spinal infection (discitis, osteomyelitis)
- Advanced osteoporosis — increases fracture risk under traction
- Aortic aneurysm or severe uncontrolled hypertension
- Pregnancy
- Cauda equina syndrome symptoms — see the red-flag box below; these require emergency evaluation
- Rapidly progressing lower-extremity weakness — requires urgent specialist evaluation
At our Louisville clinic, we do not begin decompression without reviewing available imaging and establishing a neurological baseline. If findings suggest significant nervous system dysregulation, we may sequence low-force TRT adjustments first.
If you are unsure whether you are a candidate, the clearest next step is a thorough evaluation — not a guess. Schedule a new-patient consultation at Apex Chiropractic →
⚠️ Red Flags — When to Skip Decompression and Seek Urgent Care
⚠️ Seek Emergency Care Immediately — Do Not Book a Chiropractic Appointment — If You Have:
- New loss of bladder or bowel control — sudden inability to urinate, or incontinence you did not have before
- Saddle-area numbness — in the groin, inner thighs, perineum, or genitals
- Rapidly progressing leg weakness — a leg getting weaker over hours or days, not just painful
- Numbness spreading rapidly in both legs
These may be signs of cauda equina syndrome — compression of the bundle of nerve roots at the base of the spinal cord. This is a medical emergency requiring immediate surgical evaluation. Conservative care including decompression is not appropriate. Go to an emergency room or call 911.
Herniation Type and Decompression Fit
“Herniated disc” covers several pathologies with different clinical profiles. Bulges and protrusions (disc material still contained) are the best-studied conservative candidates. Extrusions (broken through the annulus but still connected) require case-by-case review. Sequestrations (a free fragment separated from the parent disc) cannot be retracted by negative intradiscal pressure and typically warrant prompt surgical consultation.
| Herniation Type | Severity | Decompression Candidacy | Clinical Guidance |
|---|---|---|---|
| Bulge | Mild | Generally yes, with screening | Typical conservative candidate |
| Protrusion | Mild–moderate | Generally yes, with screening | Good candidate if no surgical red flags |
| Extrusion | Moderate–severe | Case-by-case; imaging review required | Surgical consultation if symptoms progressing |
| Sequestration | Severe | Generally NOT a decompression candidate | Prompt surgical consultation typically appropriate |
These categories are clinical guidance, not absolute rules. Your imaging, symptom pattern, and clinical history together determine the appropriate path.
What to Expect: Sessions, Timeline, and Realistic Outcomes
Individual sessions run 20–45 minutes. You lie on the table with a harness or pelvic belt around the lumbar spine; it applies distraction force at the specified angle, magnitude, and cycle timing. Most patients report gentle pulling — no pain. Mild temporary soreness after the first several sessions is not uncommon. Initial frequency is three to five times per week, tapering as symptoms improve.
| Phase | Approximate Timeframe | What Happens |
|---|---|---|
| Initial | Weeks 1–2 | Near-daily sessions; neurological baseline established |
| Active treatment | Weeks 3–6 | Sessions 3–5x/week; supportive exercise and TRT adjustments added as indicated |
| Reassessment | Weeks 6–8 | Clinical progress evaluated; imaging comparison if indicated |
| Supportive | Weeks 8–12+ | Reduced frequency; focus on stabilization and movement |
Patients who are good candidates and complete a full course often report meaningfully decreased leg and lower back pain. The Amjad 2022 RCT documented significant improvements at four weeks; long-term follow-up data is limited. If you have completed six to eight sessions with no meaningful change, clinical reassessment — not more sessions — is the appropriate next step.
When Surgery Is the Right Answer
Spinal decompression is not a surgery-avoidance guarantee. Some presentations require surgical consultation regardless: cauda equina symptoms, rapidly progressive motor weakness including foot drop, severe unremitting radiculopathy after 6–12 weeks of conservative care, and imaging showing high-grade nerve root compression with progressive deficits.
The SPORT trial (Weinstein et al., JAMA 2006), a multi-center study of lumbar disc herniation with radiculopathy, found both surgical and nonsurgical treatment produced improvement. Surgical patients improved faster; long-term differences between groups narrowed. Surgery produces real benefit for appropriate candidates.
At Apex Chiropractic, we work alongside primary care physicians, orthopedic surgeons, physiatrists, and spine surgeons. If a patient presents with progressive neurological findings or fails to respond to conservative care, we initiate a referral — not more sessions.
Frequently Asked Questions
Q: Does spinal decompression actually work for a herniated disc?
For appropriately selected patients, the current evidence suggests it may. Choi 2022 found statistically significant leg pain reduction and MRI-verified reduction in herniation volume versus sham. Amjad 2022 found decompression plus PT superior to PT alone. Both enrolled 60 patients; the evidence base is emerging rather than definitive.
Q: Who is NOT a good candidate for nonsurgical spinal decompression?
Contraindications: prior surgery at the affected level, spinal fracture, spinal malignancy, active spinal infection, advanced osteoporosis, severe uncontrolled hypertension, and pregnancy. Sequestered herniations and rapidly progressing motor weakness typically require surgical consultation. Cauda equina symptoms are emergencies requiring an ER.
Q: What is the difference between surgical and nonsurgical spinal decompression?
Despite the shared name, these are entirely different procedures. Surgical decompression involves a surgeon removing tissue under anesthesia. Nonsurgical decompression is a non-invasive outpatient procedure on a motorized table: no incisions, no anesthesia, no hospital stay. Same goal, different mechanisms and risks.
Q: Can spinal decompression make a herniated disc worse?
For appropriate candidates, the risk is considered low — distraction forces are computer-controlled and gradual. However, decompression is not risk-free for all presentations: patients with fracture, spinal instability, or active infection could be harmed by traction. Candidacy screening with imaging review is a prerequisite.
Q: How many sessions of spinal decompression are needed for a herniated disc?
Most protocols involve 15–20 sessions over four to six weeks, per common clinical protocols. Choi 2022 used 10 sessions over 8 weeks. Sessions run 20–45 minutes, three to five times per week initially, tapering as symptoms improve. If meaningful improvement has not occurred after six to eight sessions, clinical reassessment is the appropriate next step.
Q: How do I find out if spinal decompression is right for me in Louisville?
The reliable way to assess candidacy is comprehensive in-person evaluation. At Apex Chiropractic in Louisville, we begin with a thorough history, a 3-Part NeuroTech Exam including HRV and SEMG baselines, and review of any available imaging before recommending any protocol. We serve Louisville, Lafayette, Superior, Broomfield, and Boulder County. New-patient specials at co.apexchiroco.com/chironp-7861.
Visit Apex Chiropractic in Louisville
A first visit begins with a thorough neurological assessment — including HRV and SEMG baselines — and an honest conversation about whether spinal decompression, TRT adjustments, or another care path makes sense for your presentation. No pressure, no predetermined protocol. Check current new patient specials or call to book.
Apex Chiropractic · 183 S Taylor Ave, Unit 162, Louisville, CO 80027 · (720) 328-1790
Hours: Mon–Thu 11:00 AM–1:00 PM & 3:00–6:00 PM · Fri closed
Sources
- Choi E, et al. “Effect of Nonsurgical Spinal Decompression on Intensity of Pain and Herniated Disc Volume in Subacute Lumbar Herniated Disc.” Int J Clin Pract. 2022;2022:6343837. PMC9553669
- Amjad F, et al. “Effects of non-surgical decompression therapy in addition to routine physical therapy on pain, range of motion, endurance, functional disability and quality of life versus routine physical therapy alone in patients with lumbar radiculopathy.” BMC Musculoskelet Disord. 2022;23(1):255. PMC8924735
- Apfel CC, et al. “Restoration of disk height through non-surgical spinal decompression is associated with decreased discogenic low back pain: a retrospective cohort study.” BMC Musculoskelet Disord. 2010;11:155. PMC2912793
- Qaseem A, et al. “Noninvasive Treatments for Acute, Subacute, and Chronic Low Back Pain: ACP Clinical Practice Guideline.” Ann Intern Med. 2017;166:514–530. DOI: 10.7326/M16-2367
- Weinstein JN, et al. “Surgical vs Nonoperative Treatment for Lumbar Disk Herniation: SPORT Trial.” JAMA. 2006;296(20):2441–2450. PubMed 17119140
About the Author
Dr. Shane Kurth, D.C., BCN is the founder of Apex Chiropractic in Louisville, Colorado, board-certified in chronic intractable pain and neuropathy. A graduate of Auburn University with a degree in microbiology, he uses the research-driven Torque Release Technique alongside nonsurgical spinal decompression and coordinated conservative care. He treats patients throughout Louisville, Superior, Lafayette, Broomfield, Erie, and the greater Boulder area, coordinating with primary care physicians, orthopedic surgeons, physiatrists, and spine surgeons when cases warrant multi-provider care. Learn more about Dr. Kurth →


Ready to See the Best Chiropractor in Louisville, CO?
Apex Chiropractic believes in thriving through life, not suffering in it. We believe that the activities that we want to partake in do not only desire but are necessary, just as necessary as our daily activities. In order to thrive in life and not suffer, we have to be completely in tune with our bodies. Schedule your appointment with us, today.